Alexander Disease, and the First Drug Approved to Treat It
SEPTEMBER 21, 2026
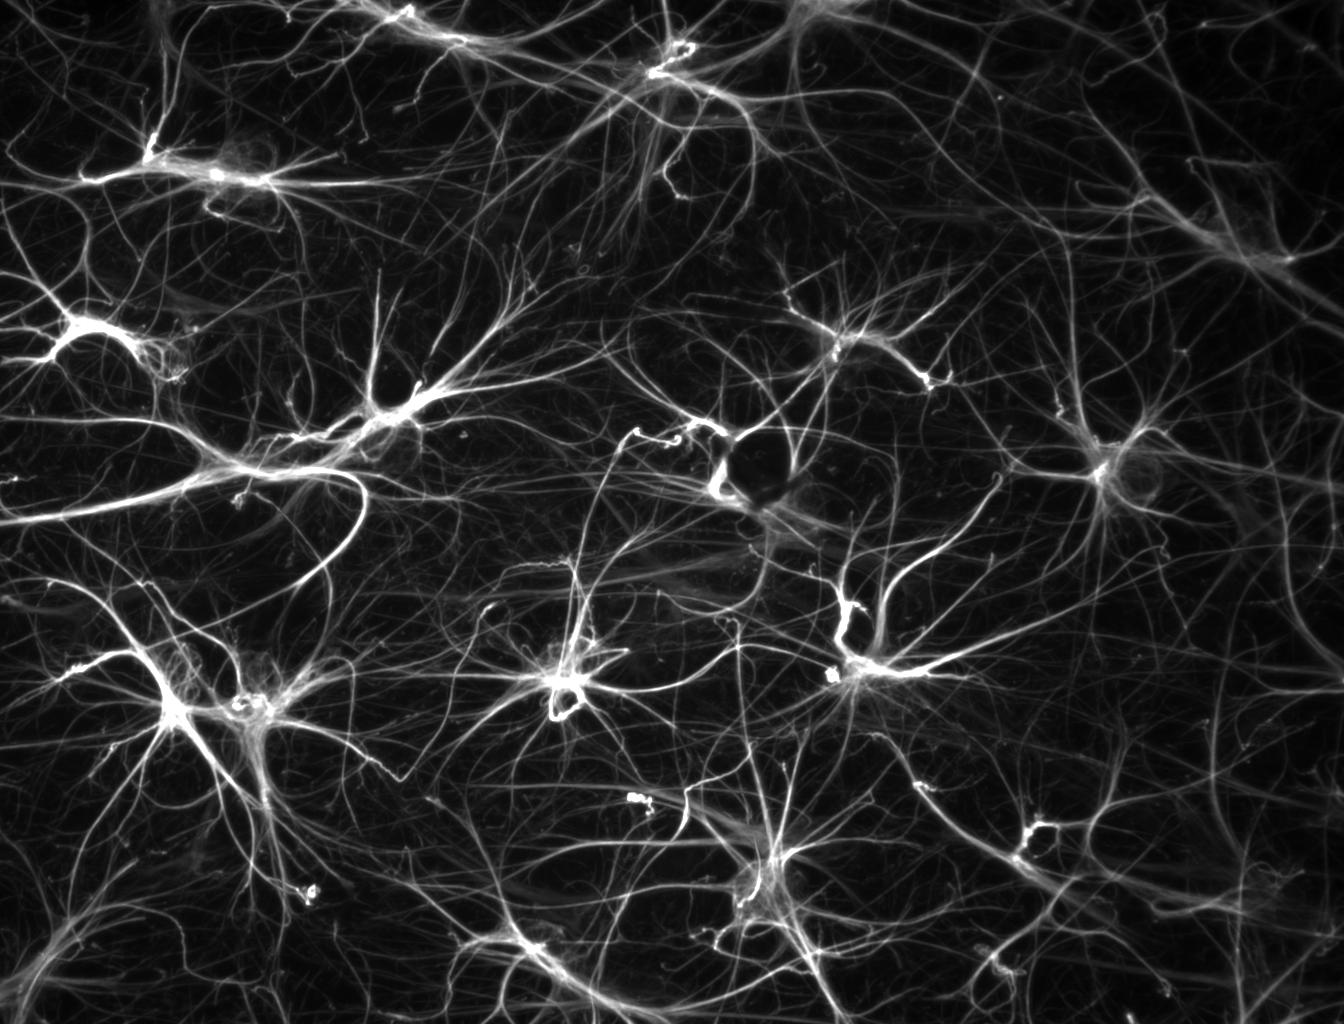
On September 3, 2026, the FDA approved Zanvastro (zilganersen) for Alexander disease — an ultra-rare, progressive and usually fatal neurological disorder that most people, reasonably enough, have never heard of. It is the first approved treatment of any kind for the disease, and the first aimed at what actually causes it rather than at managing what it does. The trial behind the approval found that patients on the drug held their walking speed roughly steady over about a year while the control group's declined. That is a real result and a modest one, and both halves of that sentence deserve unpacking — starting with what the disease is.
What Alexander Disease Actually Is
Alexander disease (AxD) is caused by a mutation in a single gene, GFAP — identified in roughly 95% of diagnosed cases. That gene codes for glial fibrillary acidic protein, a structural filament protein made almost exclusively by astrocytes — the star-shaped support cells of the brain and spinal cord. Astrocytes are not the cells that fire; they are the cells that keep the firing cells alive, regulating the chemical environment around neurons, supporting the blood-brain barrier, and helping maintain myelin, the insulating sheath that lets nerve signals travel fast.
The mutation is dominant — one bad copy is enough — and it does not simply switch the protein off. It makes a version of GFAP that the cell overproduces and cannot clear, so the protein accumulates inside astrocytes as dense clumps called Rosenthal fibers. These are the disease's pathological signature, present in every case, and they were described in brain tissue decades before anyone knew which gene was responsible. Astrocytes stuffed with malformed filaments stop doing their job properly; neurons and myelin degenerate downstream. This is why AxD is best described as an astrogliopathy — a disease of the support cells — rather than as a disease of the neurons that visibly fail. Most cases arise from a brand-new mutation in the affected child, not inherited from either parent, which is part of why families almost never see it coming.
Clinically it is usually split by age of onset. Type I begins by about age four and is the more severe course: developmental delay, seizures in roughly 90% of cases, an enlarging head, stiffness, and trouble with feeding and swallowing. Type II begins after age four — sometimes well into adulthood — and looks different enough that it is frequently mistaken for something else: progressive ataxia (loss of coordination) in about 75%, bulbar signs affecting speech and swallowing in about half, spasticity in about a third. Adult-onset AxD is misdiagnosed as multiple sclerosis often enough that it is a documented pattern rather than an anecdote. Diagnosis rests on MRI findings plus a genetic test confirming a GFAP variant.
How rare is it? The usual published figure is about one case per million births; Ionis, the drug's maker, cites one in one to three million people worldwide and estimates roughly 300 patients in the entire United States. Prognosis varies with onset — earlier is generally faster — and the company's own summary puts death at typically 14 to 25 years after symptoms begin. Before this approval, there was no treatment for the disease itself. Care meant anti-seizure medication, feeding support, physical therapy, and managing complications as they arrived.
What Zilganersen Is and How It Works
Zilganersen is an antisense oligonucleotide, or ASO — a short, chemically stabilized strand of synthetic genetic material designed to bind one specific messenger RNA inside the cell. Here the target is the RNA transcript for GFAP itself. Bind that transcript and the cell degrades it instead of translating it, so less GFAP protein gets made. The logic is direct: if the disease is driven by too much of a malformed protein accumulating in astrocytes, make less of the protein. That is why the FDA and the company both describe it as disease-modifying rather than symptomatic — it acts on the mechanism, not the consequences.
The delivery is the awkward part, and it is inherent to the drug class rather than a flaw in this particular molecule. Oligonucleotides of this kind do not cross the blood-brain barrier, so a CNS ASO has to be injected directly into the spinal fluid. Zanvastro is given intrathecally — a lumbar puncture, the same procedure as a spinal tap — at 50 mg, once every 12 weeks, by a trained clinician. Quarterly is genuinely infrequent for a drug delivered this way, but it is still four spinal procedures a year, indefinitely, for a lifelong condition.
The Trial Behind the Approval
The approval rests on one study: NCT04849741, a global phase 1–3 randomized, double-blind, placebo-controlled trial run across 13 sites in eight countries. Forty-nine patients aged two and older were randomized 2:1 to zilganersen or placebo for a 60-week double-blind period, alongside a separate open-label substudy of four children under two — roughly 53 people in total, spanning ages from about eighteen months to 53 years. Everyone who completed the blinded period could move into an open-label extension on active drug, which is the standard ethical arrangement for a trial in a fatal disease with no alternative.
The primary endpoint was percent change from baseline in gait speed on the 10-Meter Walk Test — exactly what it sounds like, timing a patient walking ten meters — measured at week 61 in patients aged five and up who had walking difficulty at baseline. The result: a least-squares mean difference of 33.3% in favor of the drug, p=0.041. In plain terms, treated patients held roughly steady while the control group's walking speed fell by about a third over the year. The statistical margin is worth noticing — p=0.041 clears the conventional 0.05 threshold, but not by much.
A secondary measure covered the children too young for a walk test. In the two-to-four-year-old group, scores on the Gross Motor Function Measure-88 — a standard 88-item scale of sitting, standing, walking, running and jumping — were 22.9 points better on drug than control at week 61, with a nominal p-value of 0.034. "Nominal" is doing real work in that sentence: it means the p-value was not adjusted for testing multiple endpoints, so it is supportive evidence rather than a second independent proof. Patient, caregiver and clinician impression scores also favored the drug, with roughly a third of treated patients rating their main symptom "much better" versus none in the control group.
On safety, most adverse events were mild or moderate, and serious treatment-emergent events were less frequent on drug than on control — which is less surprising than it sounds when the control arm is a group of people with an untreated progressive disease. The reactions reported in at least 25% of treated patients and more often than control were vomiting, back pain, cough, headache and post-lumbar-puncture syndrome; the last three are largely what a quarterly spinal tap feels like. The one finding that carries real weight is aseptic meningitis, reported in some patients, including one serious case during the blinded period that required interrupting dosing and pre-treating with dexamethasone afterward.
What the FDA Required, and What It Didn't
Zanvastro arrived carrying nearly every rare-disease designation the agency offers: Orphan Drug, Fast Track, Breakthrough Therapy, and Rare Pediatric Disease. Those are procedural accelerants — more FDA meetings, rolling review, a shorter clock — rather than a lower evidentiary bar. Priority Review set a decision date of September 22, 2026; the approval landed on September 3, nearly three weeks early.
The distinction that matters most is what the approval was not. The FDA's announcement describes a conventional approval on a clinical endpoint — how fast patients walked — not an accelerated approval based on a surrogate biomarker. That is a meaningfully higher bar than Ionis's own Qalsody cleared for SOD1-ALS, which was approved on a reduction in a blood protein with clinical confirmation still to come. Here, the agency accepted a functional measure of a person's actual movement, from a single trial of 49 randomized patients. For a disease with maybe 300 patients in the country, a single trial is not a shortcut — it is close to the entire feasible study population.
The long apprenticeship of antisense. The idea behind zilganersen — a short synthetic strand that silences one RNA transcript — was demonstrated in the late 1970s and spent most of the 1990s and 2000s as the technology that was perpetually about five years away. Ionis (formerly Isis Pharmaceuticals) was founded in 1989 to pursue it and spent a quarter century mostly not having an approved blockbuster to show for it. It now has eight marketed medicines, including Spinraza for spinal muscular atrophy — a drug that turned a leading genetic cause of infant death into a manageable condition — plus Qalsody, Wainua, Tegsedi, Waylivra, Tryngolza and Dawnzera. The platform's advantage in ultra-rare disease is that once the chemistry is solved, the next drug is largely a matter of changing the sequence to match a different gene, which is why one company keeps showing up in these announcements.
The Company, the Price, and 300 Patients
Zanvastro is notable inside Ionis for a commercial reason as well as a scientific one: it is the company's first neurology medicine it is launching itself in the United States. Spinraza and Qalsody were both partnered with Biogen, which meant Ionis took royalties while someone else ran the commercial operation. Outside the U.S., Ionis licensed zilganersen to Recordati in June 2026 for $30 million up front plus royalties, with European and Japanese submissions expected in 2027. Approval also earned Ionis a Rare Pediatric Disease Priority Review Voucher — a transferable ticket that shortens the FDA's review clock on some future application from ten months to six. Those vouchers are sold on an open market; recent ones have gone for roughly $150 million to $200 million. Ionis says it has not decided whether to use or sell it.
Then the number that will define the story for families: Zanvastro's list price is $285,000 per dose, which at four doses a year is about $1.14 million annually before rebates or discounts. That is high even by ultra-orphan standards, and it is worth being honest about the arithmetic behind it rather than merely appalled by it. With about 300 U.S. patients, there is no volume to spread development costs across; one Wall Street analyst projects peak U.S. sales of roughly $160 million in 2040, which is a rounding error for a large pharmaceutical company and would not by itself justify a fifteen-year development program. The rare-disease pricing model exists precisely because the alternative — nobody develops the drug at all — was the status quo for Alexander disease until three weeks ago. Whether a system that pays a million dollars a year per patient is the best available way to fund that is a fair argument, and not one the trial data can settle. What families will actually pay depends on insurance coverage and the manufacturer's assistance program, not on the list price, and that is where the real uncertainty sits right now.
Investors, for their part, were unmoved: Ionis shares slipped rather than rallied around the approval and the stock trades near half its 52-week high, after two large phase 3 failures earlier in the year and a sharp revenue decline. A first-in-disease approval for 300 patients is a landmark for those 300 families and a modest line item on a balance sheet. Both things are true at once.
What the trial actually showed. In one randomized, placebo-controlled trial of 49 patients, zilganersen (Zanvastro) stabilized walking speed in Alexander disease patients aged five and up over 61 weeks — a least-squares mean difference of 33.3% on the 10-Meter Walk Test, p=0.041, against a control group whose walking speed declined. In children aged two to four, gross motor scores were 22.9 points better than control (nominal p=0.034). The drug reduces production of the GFAP protein that causes the disease, so it acts on the mechanism rather than the symptoms — but "stabilized over roughly one year" is what was demonstrated. It is not a cure, it does not correct the underlying GFAP mutation, and no data yet exists on what happens over five or ten years.
Where I Could Be Wrong
- Forty-nine randomized patients is a very small trial. It is also close to the maximum obtainable for a disease affecting perhaps 300 Americans, which is exactly why regulators accepted it — but a single trial this size can produce a real-looking result by chance more easily than a large one, and a p-value of 0.041 is not a comfortable margin.
- The full study has not been through independent peer review. The efficacy numbers here come from the FDA's approval announcement, the sponsor's press releases and its conference presentation. Those are not nothing, but they are not the same as a published paper that outside reviewers have picked at.
- Sixty-one weeks is the entire evidence base for a lifelong disease. Whether the stabilization holds, plateaus, or erodes over years is genuinely unknown; the open-label extension is running and will answer it in time, not now.
- "Walking speed held steady" is not the same claim as "the brain stopped degenerating." A functional motor endpoint is a good and meaningful measure, but I am inferring that a gait-speed effect reflects slowed disease, and the trial measured the walking, not the astrocytes.
- The 2-to-4-year-old result is weaker than it reads. A 22.9-point GMFM-88 difference in a handful of very young children, on a nominal p-value in a secondary analysis, is a promising signal — the kind that should be confirmed rather than quoted as established.
- Pricing and access details may shift. The $285,000-per-dose figure is the announced list price as reported in trade press; net prices after rebates are not public, and what any given family faces will be set by their insurer and by the manufacturer's assistance program.
Sources
- U.S. Food and Drug Administration. FDA Approves First Drug to Treat Alexander Disease. 3 September 2026. fda.gov
- Ionis Pharmaceuticals. ZANVASTRO (zilganersen) approved by the FDA as the first and only disease-modifying treatment for Alexander disease (AxD) in pediatric and adult patients. 3 September 2026. press release
- ClinicalTrials.gov. Study NCT04849741 — A Study to Evaluate the Safety and Efficacy of Zilganersen (ION373) in Patients With Alexander Disease (AxD). clinicaltrials.gov
- Ionis Pharmaceuticals. Ionis presents new data from pivotal study of zilganersen in Alexander disease (AxD) at AAN 2026 Annual Meeting — the 10-Meter Walk Test and GMFM-88 figures. April 2026. ir.ionis.com
- National Organization for Rare Disorders. Alexander Disease — GFAP, Rosenthal fibers, type I and type II, prevalence and prognosis. rarediseases.org
- Quinlan RA, Brenner M, Goldman JE, Messing A. GFAP and its role in Alexander disease. Experimental Cell Research, 2007;313(10):2077–2087. doi:10.1016/j.yexcr.2007.04.004
- Hagemann TL, Powers B, Lin N-H, et al. Antisense therapy in a rat model of Alexander disease reverses GFAP pathology, white matter deficits, and motor impairment. Science Translational Medicine, 2021;13(620):eabg4711 — the preclinical work behind a GFAP-targeted antisense drug. doi:10.1126/scitranslmed.abg4711
- MedCity News. FDA Approves Ionis Pharma Drug, the First for Ultra-Rare Alexander Disease — list price, U.S. patient estimate, Recordati terms, analyst sales projection. September 2026. medcitynews.com
- STAT News. FDA approves Zanvastro from Ionis, first drug for Alexander disease. 3 September 2026. statnews.com
- U.S. Food and Drug Administration. Rare Pediatric Disease Designation and Priority Review Voucher Programs. fda.gov
- The Motley Fool. Investors Dumped Ionis Pharmaceuticals Stock — But Wall Street Hasn't Budged From Its Bullish Outlook. 20 September 2026. fool.com
This is one reader's reading of the research, not medical advice. If something here touches on your own health, take it to a clinician who knows you — and read how these entries are put together.